15.11.10

COTW: Decision-Making

A few weeks ago, we admitted a 3-month old child, reportedly previously healthy as well as previously unimmunized. After getting the story of the illness and examining the child, the most likely diagnosis was Pertussis, or Whooping Cough. She was put on oxygen and started on antibiotics.

A couple days later, she began to get worse with her breathing, and it became evident that if she was going to survive, she would need to be put on the ventilator to assist her breathing. Having no other option, we did this, with the help of our visiting Respiratory Therapist from Canada.

The next few days were extremely touch-and-go, but she persevered. We knew that Pertussis can take a while to resolve, and so weren't surprised that she didn't seem to be able to yet come off of the ventilator.

We decided to get a chest x-ray. This was her first chest x-ray, which may surprise you, but we go to great lengths to preserve cost for our patients (and that's another conversation). Here is our xray.
The most obvious thing about this xray is that the heart (the white part in the center and to the right) is huge, at least twice the size that it should be. The most careful observer (with a higher resolution image) might also notice that the ribs and spine have multiple anomalies, likely from birth, including hemivertebrae and fused ribs. Putting this all together, what we see is that she is extremely likely to have been born with a heart malformation. Thus, she may have Pertussis, before even before that (and thus, after it as well), she would not be healthy, but rather has a condition that has likely no recourse to fix here in rural Kenya.

So, now what do we do? We could keep her ventilated, try to improve her heart with medicines, and hopefully get her off the machine, but even if she managed to get discharged home, her days are extremely limited.

In the meantime, her family is accumulating a big hospital bill, which means food and school fees for the other children at home may have to go unsupplied. This issue of cost is marked here. In the US, it's frustrating that we spend 15% of GDP on health care, but no one is missing out on life necessities because of a hospital bill. And keeping her here means that 1 of 2 ventilators is occupied, and 1 of 6 ICU beds is occupied, and terribly sick patients are showing up all the time.

Our training didn't teach us how to answer this question. And, in this scenario and culture, discussing the options with the family in order to let them make their own decision is not an adequate solution for a number of reasons.

We face these questions very often, ones that matter intensely for patients and families, and for which we aren't certain of the right answer, and no one can supply us the right answer.

Pray that we would have wisdom.

13.11.10

Appropriate Technology?

When I first arrived at Tenwek, I remember being amazed at how well equipped they were for a missions hospital in the developing world. They have ventilators! They have a defibrillator (machine that gives the heart a shock, used in life support stuff)! They have scopes of all sorts--for endoscopy (looking into the stomach), colonoscopy, cystoscopy (bladder), and laparascopy (abdomen/pelvis). This is the biggest shocker--we have cardiac teams come out a couple times a year and somewhere in the recesses or the OR basement is a BYPASS MACHINE. Seriously? This is a machine that is used in open heart surgery and basically acts as a heart and lungs for the patient undergoing surgery. Unexpected.

Also, because of the various teams of surgeons that come through Tenwek, people are always brining new equipment with them to donate to the hospital. We recently got something called a Ligasure donated to the hospital. It is a clamp used in surgery that also employs electrocautery to seal any blood vessels in your clamp. Most hospitals in the US have them, but I'll bet most hospitals in the developing world don't. I've used it. It's great!

But sometimes I have to stop and wonder about how appropriate all this stuff is. When I can use cutting edge technology to do a hysterectomy (which is nice, but the surgery can also be done with far more basic equipment), but I can't find a simple metal speculum to examine my OB patient, or a clean sheet to put on the bed for her, is there something wrong? Should we be focused more on stocking the basics needed to provide better patient care before we move on to high tech? Or should we say, hey, the Ligasure was a free donation! Use what ya got!
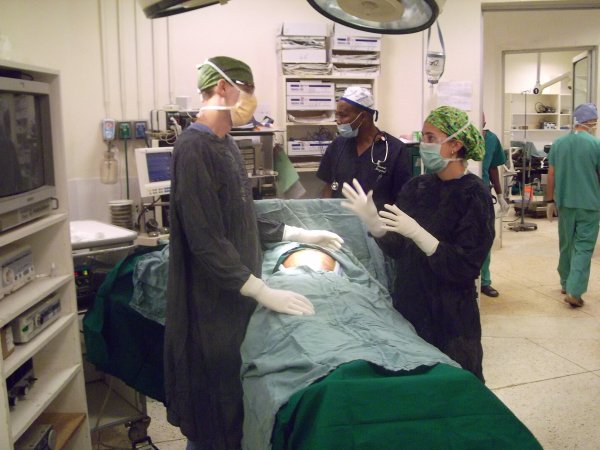
One of my former OB attendings, Bryan Popp, is now working with me at Tenwek. He was known as somewhat of a laparoscopic guru, and I was looking forward to doing some L/S cases with him to keep up my skills. Above is a photo of us doing our first laparoscopic case together. It looks like we are engaged in great medical discussion about how to care for the patient, but instead, we are shooting the breeze while waiting for the L/S stuff to get set up. About 45 minutes after the patient was put to sleep, we still hadn't started, because of some problem with the carbon dioxide gas valve. In fact, we ended up just making a small incision and doing an open case. Other L/S cases have been cancelled for similar reasons. We have the technology, but sometimes don't have the ability to maintain it or work with it. So, I could keep trying, or I could decide that what works in the US and is "best" for the patient, might not work or be the best option for my patient at Tenwek. And there are also issues about WHO gets to take advantage of the technology. When you have ventilators, but only two, which patients should get them? The sickest patients? The youngest? The ones most likely to get better? We're still trying to figure out some of this stuff...it's an ongoing process. Hopefully we'll have some more blogs in the future addressing some of these issues as well.

8.11.10

Off to Liberia

John & I are sitting in the Nairobi airport right now waiting to depart for Monrovia, Liberia.  We are excited about embarking on the third McCropder exploration trip.  Please keep us in your prayers over the next week.  Here are some specific requests:

1)  Safety in travel (both in the air and on the ground)
2)  Beneficial meetings with medical workers and government officials
3)  Health and peace for Elise & Micah who are staying at Tenwek with trusted friends
4)  Clear direction from the Lord as to whether this is a good fit for the McCropders

We'll post an update when we return.

7.11.10

COTW: Operating Together

John and I have had a few occasions to operate together, which is a unique opportunity for a General Surgeon and an Ophthalmologist. On one such case, an older gentleman came in having been stabbed through the eye and into the brain. He didn't come into the hospital for a few weeks until he had persistent pus coming from around his eye. He also had headaches and fevers. So we sent him 3 hours away to get a CT scan of his head, and he came back with a scan which showed an abscess in his brain, as well as around his eye.


So John and I did a tag team operation. I started by drilling a 3/4" hole in his head around where the abscess was. Then Rachel's department lent us a gynecologic ultrasound probe (thus involving three McCropder doctors in this operation) to look through the hole and locate the abscess. Probing a needle into the abscess under ultrasound guidance, I drained a few cc's of pus. After I closed up his head, John did some fancy eye exposure to get the pus out from around his eye. This is how he looked after we finished:

He did well after the operation and some IV antibiotics. We look forward to our next combination case.

5.11.10

Nairobi 10K Run for Sight

It is inspiring to live in Kenya among many of the world’s fastest marathoners. We had hoped that Kenyan residency would naturally boost our running speed. Alas, we will never be able to run like Kenyan runners, but hey, we’ll join in the run anyway. Last weekend, about two dozen people from Tenwek enjoyed a 10-kilometer run in Nairobi. This annual Run for Sight Event (which includes a Marathon, 10K, and Family Fun Run) donates all proceeds to support pediatric eye surgery at various eye hospitals in Kenya, including Tenwek Eye Unit. An impressive number of Eye Unit staff participated in the event. So we loaded up the Eye Unit bus and also the McCropder-mobile and headed to the races.
The morning of the race, our energy and enthusiasm could not be dampened, even when we found ourselves completely lost on uncharted roads of downtown Nairobi.
Just in time, we arrived, parked, and paused for a pre-race picture. L to R: Alyssa, Todd, Jason, Heather, Jessica, John, Toanh, and Bryan.
En route to the starting line, John found a new friend. A Michigan cap is ample grounds for friendship in any country, right?
We found our places at the starting line…
among a very large crowd. More than 14,000 other people also wanted to participate in the Run for Sight. This is Kenya, after all.
A few notes of interest about Nairobi 10K race attire: Running shoes are optional. Running in boots is ok. Running in jeans is also acceptable (see runner to left of center below… and note that he is ahead of us). And evidently, racing in the official race t-shirt is not a faux pas here.
Along the route, a super-size billboard of Michelle Obama cheered us on towards the finish line.
While the women in our group ran together at an enjoyable pace, chatting our way through 10 kilometers, the men ran at faster race paces. Note John and Bryan running with speed that made the picture blurry.
We were all glad to find each other again at the finish line, tired, happy and injury-free.
This week, back at Tenwek, unofficial training has begun for future participants in the Run for Sight.

3.11.10

ONLINE GIVING!

After more than a year working with Samaritan's Purse, we are pleased to announce the long anticipated arrival of online giving! We are generously supported both by SP, in the form of a salary/benefits, and by many of you. This is a way that will hopefully make it easier for you to support us financially, if you so desire. Note that if you are already monthly supporters, you don't have to change anything. And you can always continue to download the pdf file on the left sidebar link, print it out, and mail it in. If you'd like to save yourself some postage, however, go to:


Unfortunately, if you are looking for a "McCropder" link there is none. But you can type in an individual name (there's no Rachel...she's just with Eric) and type in the amount you would like to donate. It's supposedly quite easy (if you have faster internet than us, of course, which should be all of you). Thanks in advance! We couldn't do what we do without you guys.

2.11.10

Fall Festivities

There are no colored leaves, football games, orange pumpkins (only green), or cider mills to remind us of the season back home.  On Friday, we had some festivities to celebrate fall so that our children aren't totally clueless when we come back to the States.  In the afternoon the small kids came dressed in costume.  We decorated some pumpkin-shaped sugar cookies to pass out and then had some games.


The three-legged pumpkin race for the older kids...

The pumpkin roll for the younger kids.  I don't remember who came in first.  I just remember being amazed at how far behind Elise was!


Bobbing for apples...


Pin the nose on the jack-o-lantern...


After the games, the younger kids went on a trick or treat scavenger hunt where they had to solve clues to figure out which house to visit next.  Of course, Maggie, Abi, & Micah weren't much help, but they reaped some of the benefits!


Here's Abi sharing some of her loot with Little Bo Peep....SIKE.  She plopped it in her own mouth immediately after the picture was taken!


In the evening, the older kids gathered in their costumes to embark on a treasure hunt.  For each house that they visited, they listened to a sound (toilet flush or creaking door for example) and filled it in on their list.  They also received a clue to tell them which house to go to next.  At the end, they unscrambled the letters from their sounds to figure out where the final party would take place.


John & Jason added some spice to things by scaring the bejeebers out of the kids while they were visiting the different houses.  After the treasure hunt, we gathered on the Roberts' porch for some s'mores by the fire (Cadbury instead of Hershey and digestive biscuits instead of graham crackers).  We concluded with a creepy story in the dark that involved spaghetti noodles for intestines and olives for eyeballs.  It was a fun day and the kids had a blast.    

Happy Fall to everyone!  Indulge in an extra donut and some cider for the McCropders.  :)

28.10.10

Budding Ballerinas

With so many little girls around, there are many "girlie" activities going on all the time around the McCropder-plex at Tenwek. Not so many days ago, Elise Cropsey, Anna Fader, and Hannah Bemm all got on their ballerina skirts. Maggie McLaughlin joined in the action (by putting on her bathing suit). The girls were all posed and ready for their photo shoot in front of a bush when some biting ants made their appearance. Hysterics ensued. Then calm. And a re-posing in a safe place by the stairs. :)

25.10.10

Truth is Stranger than...

Our friend James Paternoster sent us this story...a TRUE story, which occurred just recently in the DRC (Congo). Read on and be amazed.


A small airliner crashed into a house, killing a British pilot and 19 others after a crocodile smuggled into the aircraft in a sports bag escaped and started a panic.

It has now emerged that the crash was caused by the concealed reptile escaping and causing a stampede in the cabin, throwing the aircraft off-balance.

A lone survivor apparently relayed the bizarre tale to investigators.

The crocodile survived the crash, only to be dispatched with a blow from a machete.

Danny Philemotte, the Dutch pilot and 62-year-old owner of the plane's operator, Filair, struggled in vain with the controls, with Chris Wilson, his 39-year-old First Officer from Shurdington, near Cheltenham, Glocs. The plane was on a routine flight from the capital, Kinshasa, to the regional airport at Bandundu when the incident unfolded, on August 25. It crashed into a house just a few hundred feet from its destination. The occupants of the property were outside at the time.

According to the inquiry report and the testimony of the only survivor, the crash happened because of a panic sparked by the escape of a crocodile hidden in a sports bag. One of the passengers had hidden the animal, which he planned to sell, in a big sports bag, from which the reptile escaped as the plane began its descent into Bandundu.

A report of the incident said: "The terrified air hostess hurried towards the cockpit, followed by the passengers." The plane was then sent off-balance "despite the desperate efforts of the pilot", said the report. The plane was a Czech-made Let L-410 Turbolet, one of more than 1,100 produced as short-range transport aircraft and used mainly for passenger services.

http://www.telegraph.co.uk/news/worldnews/africaandindianocean/democraticrepublicofcongo/8078612/Aircraft-crashes-after-crocodile-on-board-escapes-and-sparks-panic.html


23.10.10

Tanzania Surgical Safari 2010: To Tanganyika and Back Again

I'll be honest, life's been a bit crazy lately and the impending Tanzania (TZ) trip wasn't helping much in that category.  For the past six months I had been struggling with bureaucracies to get a Tanzanian medical license despite having spent a lot of money.  I was tired enough that the prospect of not getting my license and having to cancel the trip actually had a bit of appeal.  But, sure enough, my medical license was approved with just a bit of time to spare.  Then there was packing. 

The week leading into the expedition I was away at a much needed retreat in Mombasa and could not be involved in packing whatsoever.  As I left for Mombasa, I knew we were critically low on viscoelastic (a clear gel needed for eye surgery which had been on order for 6 months and still hadn't arrived!) and our portable surgical microscope was broken.  Both are essential.  I was consciously trying to trust God and the eye staff, but the OCD devil in me sure wasn't happy.  He was saying, "Think of the 40+ person team and hundreds of patients in TZ depending on you.  Think of the thousands of dollars invested.  All it takes is one thing missing (viscoelastic, microscope, generator, blown microscope bulb with no spare, wrong power cord...) to ruin the mission." 

No worries.  Even if I wasn't feeling particularly up to going on a surgical expedition, apparently God was interested in making it happen.  The eye staff seamlessly packed without me, and honestly, they did a much better job than I could have done.  During my week away in Mombasa, a visitor from the USA brought out the part needed to fix the microscope, and, although 6 months late, we finally received our order of 1,000 vials of viscoelastic.  Wow.  So off we left for Nairobi packed into the Jolly Green Giant (perhaps her max load to date) to spend the night near the airport.


We were up at 5:00 am to catch our Cesana Caravan from Wilson Airport.


After a small hassle from the customs folks about our strange, expensive-looking eye equipment, we were in the air with AIM AIR.


After one refueling stop and 5+ hours in the sky, we officially reached the "back forty" of TZ.  Our airstrip was on the edge of Lake Tanganyika (world's longest lake) and at the foot of the Mahale Mountains which form the boundary of Mahale National Park, one of the more remote national parks in the world.  Once dropped off on its shores by airplane or boat, it is accessible only on foot. 
  

Above: the Tenwek Eye Unit team at Mahale airstrip with our fancy new scrubs.  Thanks Ben!
 

We were then transported to the local government health center by helicopter.  Our equipment had to go by boat.


As expected, the helicopter got the local kids (and me) worked-up into a frenzy.
 

The obligatory Obama twins were spotted once again, just as they were upon our landing in Akot, Sudan earlier this year (below).  


This whole trip was organized by Hope of the Nations Bible College in Kigoma, TZ.  They stopped classes for the week and boated all the students and faculty down the lake to assist us in caring for the patients physically and spiritually.  They also held kids' clubs and went into the community to mobilize the blind and share the good news of Jesus Christ, The Hope of the Nations.  Below are some of the the key organizers and docs involved. 


(Left to Right: me; Dr. Norbert - medical director of the health center who invited us; Dr. Kabadi - Tanzanian ophthalmologist and friend of Dr. Norbert, Dr. Steve Anderson - ophthalmologist joining us all the way from Indonesia; Dr. Len Ramsey - medical doc and the chopper pilot with Hope of the Nations! 
First, we settled into our abodes for the week.  My bed was strategically placed under the lake front window to absorb in sponge-like fashion as much rainfall as possible during the night storms coming off the lake.


Next, we screened the patients already waiting for us, and we got the OR up and running.  Our very first case that evening was on our own team member who gashed his hand upon arrival by falling into the lake onto sharp rocks.  Thankfully, we had a microscope for his tendon repair.  Other than some numbness of the pinky, he's got full function of the digit despite having me for his hand surgeon using ophthalmic suture.


Below: patients on post-operative day #1waiting to have their patches removed.  This is always a special time.


We had several patients originating from the other side of Lake Tanganyika (Democratic Republic of Congo, aka former Zaire).  They tended to be on the smaller size as you can see from the picture below.   
 

An Mzee quietly enjoying his first look around in a long time. 


This lady obviously has a huge goiter, but also notice the white pupils.  Those are blinding cataracts.  We did surgery on one eye with great success, but when she heard that her doctor loved Jesus, she was a bit upset.  She was Muslim and couldn't believe someone who loved Jesus would do something like that for her.  She did get over her perplexity and had her other eye done at the end of the week.  She was seeing 20/25 when she left!  She begged us to remove her goiter, but obviously, this was not the setting to attempt such a feat.  


Below is another woman who was accompanied by her daughter and granddaughter.  She left one happy grandma. 


This is the last day's post-ops.  They were a particularly fun group.


All in all, we saw over 400 patients.  Many were given their sight back just with simple glasses that could not otherwise be obtained easily in this area, but seventy eyes needed surgery (mostly cataracts) in order to see again.  Many heard about Jesus for the first time in this mostly Muslim area, and many professions of faith were made.  Ten were baptized publicly on the shore of their village on the last two days of the outreach.  God was touching the lives of these folks indeed.  

I, too, was deeply refreshed during the quiet morning hours spending time in prayer and God's Word at the lake's edge.  God needed me to have my vision for life and ministry renewed as well.  God didn't need me to go on the trip.  I needed to be on the trip.


As I sailed away from this little peninsula for the airstrip, it was evident that God had been at work in me and through me, despite of me.  God is good.  Thanks for all of your prayers.